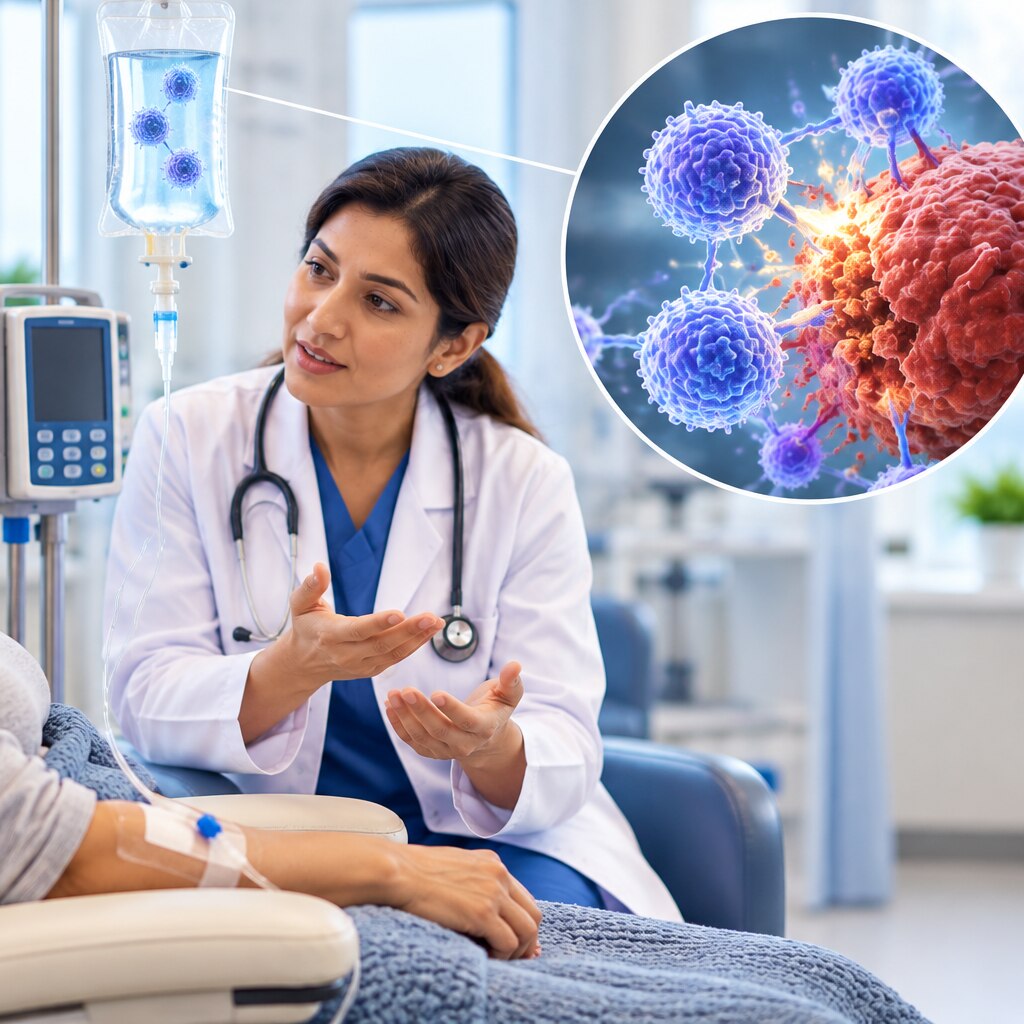
Cancer cells can avoid immune attack by switching off the T cells that might recognise them, but immunotherapy is designed to interrupt that escape or provide immune cells with new instructions. By the end, you will understand how these treatments work, who may benefit, what treatment involves, which warning signs require urgent help, and what to ask before agreeing to therapy.
Key takeaways
- Immunotherapy helps immune cells recognise or attack cancer cells.
- Biomarker tests can show whether immunotherapy is suitable for your cancer.
- Report breathing problems, severe diarrhoea, confusion, or yellow skin urgently.
- Ask about infusion timing, scan dates, monitoring tests, and treatment costs.
How immunotherapy turns an immune response against cancer
Immunotherapy is cancer treatment that helps your immune system recognise, activate against, or sustain an attack on cancer cells. Unlike many chemotherapy drugs, it does not directly kill every cancer cell. Instead, it strengthens or redirects immune activity so your own defences can do more of the work.
The term covers several treatment approaches, and each works differently.
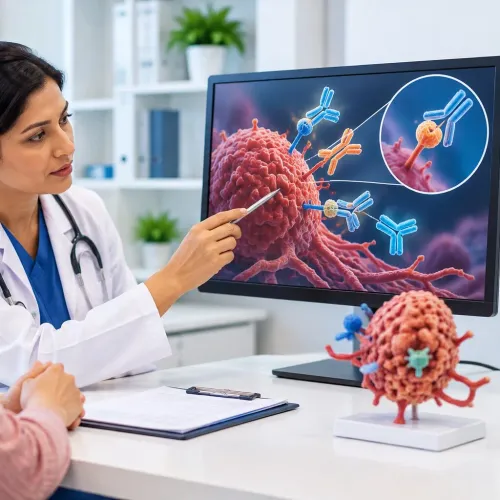
Immune-checkpoint inhibitors target “brakes” that restrain T cells:
- PD-1: a brake on T cells; its partner, PD-L1, can be displayed by cancer cells or nearby immune cells to weaken the attack.
- PD-L1: blocking this signal prevents cancer cells from switching off T cells through the PD-1 pathway.
- CTLA-4: a checkpoint that limits T-cell activation early in the immune response; blocking it can increase T-cell activation.
After treatment blocks these inhibitory signals, T cells can recognise cancer-related markers, multiply, enter the tumour, and release substances that damage cancer cells. The treatment does not guarantee that every tumour will respond: some cancers lack a useful immune target, hide their markers, or develop resistance after an initial response.
Because the same immune brakes protect healthy tissue, releasing them can cause activated immune cells to attack normal organs. New diarrhoea, breathlessness, jaundice, severe rash, or unusual fatigue during treatment needs prompt contact with the oncology team.
Which cancers and patients may be suitable
An eligible cancer is not enough to make immunotherapy appropriate. The cancer’s origin and stage determine whether a checkpoint inhibitor, cellular therapy, or another immune-based treatment has evidence behind it.
Melanoma, non-small-cell lung cancer, kidney cancer, and bladder cancer are among cancers in which checkpoint drugs may be used, but eligibility changes with localized versus metastatic disease and previous treatment. Surgery or radiotherapy can remain the better first choice for localized disease.
| Factor | How it changes suitability | What clinicians review |
|---|---|---|
| Cancer type and stage | Determines whether the drug is approved or supported by evidence | Tumour origin, spread, and resectability |
| Biomarkers | Can identify a higher-likelihood group, not guarantee response | PD-L1 staining, mismatch-repair or MSI status, and sometimes tumour-mutational features; the cutoff and assay depend on the drug |
| Previous treatment | Affects the available sequence and expected benefit | Chemotherapy, targeted therapy, radiotherapy, surgery, and resistance |
| Health history | Can increase the danger of immune-related inflammation | Autoimmune disease, organ function, transplant history, infections, and current medicines |
| Treatment goal | Shapes whether benefit justifies delay or toxicity | Cure after surgery, disease control, symptom relief, or extending life |
A PD-L1-positive result does not ensure response, and a PD-L1-negative tumour can still respond. A specialist must also weigh performance status, expected side effects, and alternatives; immunotherapy is not a universal replacement for chemotherapy, surgery, or radiotherapy. CAR-T therapy follows a different pathway and is mainly used for selected blood cancers under intensive monitoring.
What treatment looks like from infusion to scan
An intravenous infusion usually takes place in an outpatient unit. A nurse checks your medicines, symptoms, blood tests, and organ function before the drug enters a vein; the team then observes you for an immediate reaction. The schedule depends on the medicine, with visits commonly separated by several weeks.
Scans provide the main measurement of response, using tumour size and the appearance of new lesions. Your oncologist also considers pain, breathing, weight, energy, examination findings, and blood results. Biomarkers such as PD-L1, MSI-high status, or mismatch-repair deficiency can support treatment selection, but none guarantees a response.
Scan results use terms with specific implications:
- Stable disease: the cancer has neither shrunk enough to count as a response nor grown enough to count as progression. Holding the disease steady can be a useful outcome, especially when symptoms improve.
- Pseudoprogression: a tumour can look larger, or a new inflammatory area can appear, because immune cells have entered the cancer. True progression is more common, so repeat imaging and your clinical condition help settle the interpretation.
- Resistance: the cancer fails to respond from the start, or begins growing after an initial response. Doctors may change treatment when scans and symptoms show genuine progression.
- Stopping treatment: immunotherapy can end after planned treatment, unacceptable toxicity, confirmed progression, or a patient’s informed decision. Some responses continue after the last dose, but follow-up scans remain essential.
Side effects, monitoring, and urgent warning signs
Immune-related adverse events happen when activated immune cells attack healthy tissue as well as cancer. They can affect the skin, bowel, liver, lungs, thyroid, or other endocrine glands, causing problems that differ from ordinary chemotherapy side effects.
These reactions can begin during treatment or after it stops. Contact the oncology team promptly for:
- New or worsening diarrhoea, abdominal pain, or blood in the stool
- Breathlessness, chest pain, or a persistent cough
- Yellow skin or eyes, dark urine, or severe nausea
- A widespread or blistering rash, facial swelling, or painful skin
- Marked fatigue, dizziness, confusion, or unusual thirst and urination
Do not wait for the next scheduled visit or assume these symptoms are harmless. A mild symptom can worsen quickly, and early treatment can prevent permanent organ damage.
At each visit, report new symptoms, even if they seem unrelated. Your team may check blood counts, kidney function, liver tests, thyroid function, blood sugar, and hormone levels, along with oxygen levels and other examinations guided by your symptoms.
Treatment depends on the affected organ and severity. Clinicians may pause immunotherapy, treat the specific complication, and prescribe corticosteroids. Severe or steroid-resistant reactions can require additional immunosuppressive medicines and hospital care. Never start or stop steroids without medical advice.
Tell every healthcare professional that you receive immunotherapy. Keep an emergency contact number and treatment record with you, because immune-related toxicity can require assessment outside your usual appointment.
Choosing a plan and preparing for the practical details
Compare expected benefit, speed, side effects, logistics, and cost—not the treatment name alone. Immunotherapy may be single-agent or combined; combination checkpoint inhibitors and chemotherapy-immunotherapy can improve control for selected cancers but raise toxicity.
Targeted therapy depends on an actionable alteration, while radiation treats a defined area; surgery may be the better first treatment for removable disease. CAR-T-cell therapy involves collecting and engineering T cells, then specialist monitoring, mainly for selected blood cancers.
| Option | Practical comparison | Questions to verify |
|---|---|---|
| Immunotherapy | Infusions and immune-related effects can occur during or after treatment; response may require repeat scans | Is there a biomarker supporting this drug, how often are infusions and scans, and which symptoms require an urgent call? |
| Chemotherapy-immunotherapy | May widen treatment activity but adds chemotherapy effects to immune toxicity | What extra benefit is expected over either treatment alone, and how will dose delays be handled? |
| Targeted therapy or radiation | Targeted therapy requires a matching alteration; radiation focuses on a specific site | Is testing complete, and is local treatment needed for symptoms or control? |
| CAR-T-cell therapy | Personalised manufacturing, hospital-based care, and risks including cytokine-release syndrome and neurologic toxicity | Is referral appropriate, how long is manufacturing, and who provides monitoring? |
Ask for a written estimate covering the drug, administration, tests, admission, emergency care, travel, and follow-up. Confirm insurance authorization, assistance programmes, infusion capacity, and what happens if supply or approval is delayed. At Dr Gawande Oncocare Centre, take pathology, scan discs, biomarker reports, medication lists, and autoimmune or transplant history to the consultation.
Ask which goal defines success, when treatment stops, and whether a clinical trial or second opinion changes the choice.
Frequently asked questions
How does immunotherapy turn an immune response against cancer?
It helps the immune system recognise cancer, removes signals that suppress immune cells, or strengthens immune activity against tumour cells.
Which cancers and patients may be suitable for immunotherapy?
Suitability depends on the cancer type, stage, previous treatment, overall health, and test results such as PD-L1, MSI, or mismatch-repair status.
What does immunotherapy treatment involve?
Treatment commonly involves an intravenous infusion, observation for reactions, blood tests, scheduled reviews, and scans to assess whether the cancer is responding.
Which immunotherapy side effects need urgent medical attention?
Contact your oncology team urgently for breathing difficulty, severe diarrhoea, persistent vomiting, confusion, marked weakness, jaundice, or a high fever.